

September 3, 2026
post
Virtual Reality or Manikin-based Simulation?
In short: each has their strengths – virtual reality has the advantage on cost-effectiveness, standardization, learner autonomy, and breadth of scenarios, while VR and manikin-based simulation are comparable on skill acquisition and realism.
Manikin-based simulations can support hands-on skills and often have the benefit of working in groups. Most programs use both, matching each modality to the learning objective.

When it comes to healthcare training and education, simulation is a core component designed to apply, test, and refine clinical skills in a safe environment for the learner.
There are many ways to accomplish this, from traditional methods like manikin-based simulations and the use of standardized patients to more modern methods like virtual simulation and virtual reality.
Which is better? Or perhaps a better question is, how do you decide which is the best fit?
We’ve taken a look across five different categories, comparing VR with traditional simulation methods:
- Cost & time
- Skill acquisition
- Realism
- Standardization
- Autonomy
- Breadth of content
- Data and analytics
Cost & time
Simulation, just like anything else, costs money and time to put together. In direct comparisons, VR is the more cost- and time-efficient choice, with one study showing that VR simulation takes 22% less time and costs 40% less than physical simulation.
Much of what gets invested towards simulation is dependent on budget – what can or should a simulation lab spend to maintain or improve its simulation experiences?
Those decisions are made more individually, and depending on the equipment available and prior investments, what costs over the other can vary.
It’s no secret that manikin-based simulations take significant time to plan, set up, run, and break down. In contrast, VR simulations can be run at the push of a button and may not require a facilitator be present. This can result in enormous time savings for faculty and educators.
Take it from the institutions that realize savings of 200 hours of time and reduce costs by 74%. When it comes to cost and time savings, VR has a distinct advantage over manikin-based simulations.
Skill acquisition
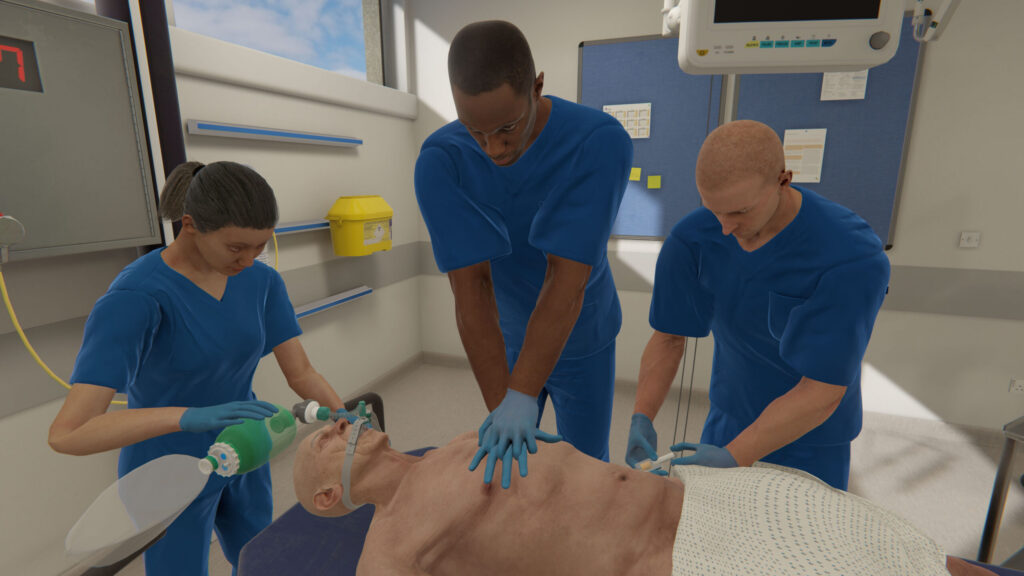
Putting VR and traditional simulation head-to-head, there’s no clear winner. Both effectively develop clinical skills, and a cost-utility analysis found that VR delivers learning and performance outcomes similar to physical simulation while being significantly less expensive – a win-win!
A 2025 systematic review and meta-analysis pooling 19 randomized controlled trials and 769 nursing students demonstrated that VR produced statistically significant gains in both knowledge and clinical skills versus control conditions.
Virtual reality is not here to replace physical simulation. All modalities of simulation have their own roles in connecting clinical concepts to application, and all should work together to support learners in their skills.
It’s important that simulation does what you intend it to, which is typically to develop, hone, or refresh clinical skills. Aligning the right modality with the appropriate learning objective is one of the best ways to ensure a meaningful learning experience.
Boston Children’s Hospital is one such institution utilizing physical and VR simulation to help staff stay prepared for clinical situations.
Jeffrey Jacobs, XR Lead, Immersive Design Systems at Boston Children’s Hospital, said of VR simulation, “We expect VR simulation to take its place alongside physical simulation as a standard means for new people to train in and also experienced clinicians to learn new things.”
The choice is yours – it’s all about which modality is the best fit for educators and learners because both virtual reality and physical simulation are effective in the development of clinical skills.

Realism
Realism is largely a draw considering both VR and high-fidelity manikins can create clinically realistic scenarios – it’s how the simulation runs that matters more than which modality you choose.
A high-fidelity manikin can do many things that a person would do and mimic many of the components of a particular condition.
Virtual reality, on the other hand, creates an immersive environment, where the learner can engage and speak with virtual patients. This is particularly true for simulations in headset, which brings another level of immersion to the simulation – something that can enhance the learning experience and bolster memory.
Many manikins or task trainers can only mimic parts of a larger whole, and when simulations are conducted in groups, it can inhibit the realism of the simulation.
In VR, the learner is individually transported into the virtual environment and works directly with a patient with a complete history and presenting symptoms. The narrative thread of a VR scenario creates a simulation where learners can get a complete picture of a patient’s status and see how their interventions impact those symptoms in real-time.
A 2025 study put the two head-to-head directly, assessing the same medical students on both an OMS VR scenario and a high-fidelity manikin, and found no statistically significant difference in performance between them. While the study was small with a sample size of 16 students, these findings align with other studies indicating both VR and manikin-based simulation result in similar learning outcomes.
When it comes to realism, there is no clear winner – both VR and manikins can create a realistic environment for simulation. However, that largely depends on how the simulation is run, whether it’s done individually or in groups, the environment of the sim lab, and other factors that can either increase or decrease the realism of the scenario.
Whether you choose VR or manikin-based simulation, there’s more work to be done to ensure it’s as realistic an experience as possible.
Standardization
For standardization, VR comes out on top: every learner in a headset or on-screen meets the identical patient, presenting the same way, with the same chance to apply their skills.
A concern for many healthcare students transitioning to practice is a limitation in clinical experiences. There can be a lot of fear around the realization that you may be caring for a patient with a condition you’ve only ever seen in a textbook.
It’s a common worry and informs the types of simulations that educators work to provide for students, but it’s nearly impossible to account for every condition a student may face.
Clinical experiences cannot be standardized – that is, not everyone will see the same conditions or get the same learning opportunities even within the same placements.
With a manikin-based simulation, often conducted in groups, it’s very difficult to recreate the exact same experience for each individual student over the course of the day.
The 9am group won’t often get the same experience as the 3pm group. Even within the group experiences can diverge. Learner A may be quieter and more observant while Learner B may be more hands-on. This results in two different experiences, even in the same simulation.
Virtual reality is a stark contrast to that. Each learner gets into a headset individually and gets the exact same simulation as everyone else. Of course, the simulations themselves may play out differently depending on what each learner does, but the fact remains that VR scenarios are inherently more aligned to standardization, particularly at scale.
When it comes to standardizing simulation experiences, virtual reality is the clear winner of the day.

Autonomy
VR gives learners more autonomy than manikin-based simulation: each trainee works the case alone, making decisions without a facilitator stepping in.
One of the clearest differences between the two modalities is how much a learner does on their own. Manikin-based simulation is often run in groups, with a facilitator guiding the scenario and peers sharing the workload. As noted above, Learner A may have a completely different take than Learner B, even when they share the same patient. In VR, the learner is alone in the headset, working autonomously with their virtual patient just as they would in practice.
There’s growing evidence that this independence has a real impact. A randomized controlled trial of 168 newly graduated nurses found that those who completed an immersive VR curriculum were significantly better at independently recognizing pediatric respiratory distress and impending respiratory failure, at both three and six months after training, than peers who received standard orientation alone (Raab et al., 2024).
Learners notice the difference too. In a multi-site study across three nursing programs, students repeatedly described valuing the chance to act as the sole clinician and to make, and learn from, their own mistakes in the simulation (Bradley et al., 2024). This underscores another key factor for virtual reality: psychological safety.
For these simulations to work as intended, learners must feel comfortable in the space, both psychologically and from a usability perspective. Not all learners are technology natives, regardless of age, so a thorough orientation and onboarding, alongside clear expectation-setting and a structured debrief remain core as part of simulation-based education.
When it comes to autonomy, VR has the edge – provided learners are set up to succeed with it.
Breadth of content
Because of the digital nature of virtual reality, it holds far more potential for breadth of content than physical simulation, which is limited often by the equipment on hand and the programming of each manikin.
In VR, a single platform can move between specialties in minutes, while each manikin scenario needs its own setup.
For example, if you wanted to pivot from an adult sepsis scenario to an obstetrics postpartum hemorrhage scenario, you would need to have a completely separate manikin for that change, and you’d need to set aside significant time to coordinate it.
Because learners can’t be guaranteed experiences in the clinical setting, this means it’s up to educators to fill the gaps and provide learners with guaranteed experiences so they can be as prepared as possible for any situation.
Manikin-based simulation is limited when it comes to breadth, because certain manikins can do certain things, and an adult manikin is an adult manikin.
With VR, scenarios can cover just about anything – there are very few, if any, limits on what a virtual reality scenario can be.
Having access to a library of scenarios, like the OMS platform with 260+ scenarios, can make switching from one specialty to another seamless.
In the above example, if you wanted to have learners first complete a sepsis scenario and then move on to an obstetrics scenario, that would take maybe a few minutes in virtual reality. You’d simply need to exit one scenario, then select another, and you’re on your way.
Plus, there’s a lot of ways you can impact, change, or edit a VR scenario with access to an authoring platform, like OMS Create.
This gives you even more flexibility in the breadth of content you can provide, giving VR the edge over manikin-based simulation.
Data & analytics
This is where VR pulls decisively ahead: it’s the only modality that can capture every action (or inaction) a learner takes and turn it into performance data, from one individual through the entire cohort.
The usual approaches to assess simulation effectiveness – competency checklists, skills fairs, preceptor sign-offs – are manual, time-intensive, and often differ between assessors. Passing an exam doesn’t necessarily equate to performing optimal patient care, particularly under a pressure-intensive clinical situation.
Because manikin-based simulation is usually facilitated in groups and scored by observation, the data that’s collected depends on who was watching and what they happened to catch. Comparing one learner to another, or this year’s cohort to last year’s, in any consistent way is nearly impossible.
Virtual reality is different. Because every learner works through the same standardized scenario on their own, the platform can capture each decision, assessment, and intervention, measuring it against the same clinical benchmarks every time. OMS goes a step further, classifying those actions into meaningful clinical behaviors and competencies, so you’re seeing how learners perform across the specific skills that matter most.
At an institutional level, that adds up to something no other modality can offer: a clear, objective view of how learners and whole cohorts are performing across clinical competencies, at scale. Instead of waiting for an end-of-placement impression, or worse – a patient safety event, to reveal a gap, educators can spot the patterns early. This data can answer questions like: Where is a cohort consistently struggling? Which behaviors need reinforcing before students reach the bedside? How is each individual student progressing towards competency?
Simulation has always been about getting and staying prepared for any clinical situation that could arise in practice. VR is the only modality that can also show you, objectively and at scale, whether that preparation is working, turning simulation from an experience into evidence of readiness.
Conclusion
When it comes to virtual reality or manikin-based simulation, one is not here to replace the other. Both have value and contribute to the learning process, and while the modalities are different, the goal is the same – to help learners bolster their skills, get and stay prepared for any situation in clinical practice.
If you’re weighing VR simulation for your program, choosing the right platform matters as much as choosing the modality. Our guide to evaluating a VR simulation partner walks through the questions worth asking before you commit.
Frequently asked questions
Is VR cheaper than manikin-based simulation?
In direct comparisons, yes. One analysis found VR simulation takes 22% less time and costs 40% less than physical simulation, and some institutions report saving 200 hours and cutting costs by 74%. VR can also run without a facilitator, adding to the savings.
Should VR replace manikin-based simulation?
No, and it isn’t meant to. Both modalities develop clinical skills effectively and have distinct strengths. Most programs use them together, matching each to the learning objective rather than choosing one over the other.
Is VR as effective as manikins for building clinical skills?
The evidence suggests they’re comparable. A 2025 meta-analysis of 19 randomized controlled trials (769 nursing students) found VR produced significant gains in knowledge and skills, and a head-to-head crossover study found no significant performance difference between VR and a high-fidelity manikin.
Which is more realistic, VR or manikins?
Both can be highly realistic. Manikins offer physical, hands-on fidelity; VR offers immersive, narrative-driven scenarios with a complete patient picture. Research suggests immersion alone doesn’t guarantee better learning – scenario design and debriefing matter more than the modality.
Does VR support independent, autonomous practice?
Yes. Each learner works through the case alone in a headset, making decisions without a facilitator stepping in. A randomized trial of 168 new nurses found VR-trained nurses were significantly better at independently recognizing patient deterioration months later.
Related



Ready to get real?
See how OMS can help your organization build confidence, competence, and clinical readiness for today’s healthcare.

